Wednesday, 10 February 2016

Medical careers - first specialist interest selection

Medical speciality decision: amusement

For the first time in the medical course we're being asked to prioritise from our areas of speciality interest (choosing 4 from 100 or so) to direct 20 days we'll spend during Year 3 of our 4-year graduate medical course.  Eeek!

Overeager?  Well, by most measures it's pretty minor this early on - what's 20 days in a 1500 day course, after all.  But there's something in it.  It's a guarantee that one day some Morpheus-like character will present the proverbial blue pill and a red pill for the speciality choice, and it'll be well to know which one to take.  Else it'll be a rerun of schooldays' UCAS with a zillion courses and little to pick between them, or the extraordinary array of projects to pick from on consulting jobsites...

So - last summer I was gathering tips from my cardiology mentor (Diane) on where next to network and get experience in medicine, and she rightly tasked me to draw out a picture of how the future might look (and where I might be for it).  Undoubtedly, one of the benefits of the medical career is the predictability of career pathways, still a tough task.

View pinged to Diane @ close of 2015

Specialities under consideration
So there are lots of options & here are three which have some appeal...

Orthopaedics (e.g. broken bones, joints, muscles, tendons): a long but practical route, takes about 15 years from med school start till consultant, which is when you're fully trained.  This 15 years would be varied - working on all different parts of the body; then the second half of the career would be potentially 15 years as a specialist hand surgeon (finer detail, get to sit down, better hours!).  It has interesting patients of all ages, you see rapid and dramatic change in the patients, hand patients are awake during the procedures, there's the important psychological angle around pain & physio adherence, and it's internationally relevant - the development agencies seek orthopaedics and there's a big demand for surgical training in the developing world.  Plus I had a great time observing this in Nairobi.  What's not to like? LINK

Infectious disease (e.g. hepatitis / meningitis / HIV / MRSA / TB): there's all the fascination of problem-solving which the medical dramas make a play on, as well as the integration of animal and human disease vectors.  And the great thing is - most diseases are controllable, so the patients tend to get better.  Naturally lots of docs deal with infections, but specialists have extra interest in hepatitis / meningitis / HIV / MRSA / unexplained fever / TB / malaria as well as the less common neglected tropical diseases.  The contagious nature also gives a significant public health component which appeals.  However, bit of a less clear career structure.  Haven't shadowed here yet. LINK LINK

Cardiology (e.g. heart murmurs, heart attacks, blocked arteries): combines some of the interesting breadth of medicine with surgery (e.g. pacemaker fitting, stenting, angiography); and I've met a couple of lovely people that work in it, my bro included.  Only trouble is, it's pretty western-world bound: it's relatively expensive to deliver and patients in poorer parts of the world tend to die before they get old enough for the complex coronary interventions.  Plenty of money available for research tho.  Plus I had a great time observing at Arrowe Park.

Of course, medicine's not all about the theatre or time with the patients.  You have to take on extra responsibility to boost your department, and I think a bit of teaching (I've always enjoyed training/lecturing) and/or management (FMLM is one related  organisation) may suit - whether research is interesting in the domain is probably a bit speciality-dependent.   Time's likely to be pressed, but I also like the idea of engaging with a more broad-reaching institution too.  That could be an international organisation with a speciality focus (e.g. an NGO like WOCUK, GNNTD or WHF), or something more cross-speciality (e.g. the APPG, King's Centre for Global Health: Surgery).  Let's not think too far ahead...

Stereotypes of the specialities (haven't held true yet in my experience)
Aside from the minutiae of which body parts you'll be working on, some say the most important consideration is whether you like the people and the team cultures in the departments you work in, as these specialities can have prevailing cultures. I'll have to see about that as I start rotating through the departments.

Orthopaedic surgeon (general stereotype: of a meaty thuggish sportsnut, well that's certainly not me)
Hand surgeon - a subspeciality of orthopaedics once you're trained (stereotype: a little softer hands, a little calmer)
Infectious disease physician (stereotype: intellectual traveller types - includes lab work tho)
Cardiology (stereotype: smartest of the lot.)

Competition in the specialities (applicants per place) after FY1 and FY2, i.e. 4 years from now for me:
Orthopaedics: 2.5:1 for core surgical training Y1-2; then 5:1 for orthopaedic specialist training Y3-7.  LINK   Alternatively 10:1 for run-through training from ST1-7
Infectious disease: 2:1 for core medical training Y1-2; then 2:1 specialist training Y3-6 + PhD LINK
Cardiology: 2:1 for core medical training Y1-2; then 6.5:1 for specialist cardiology training Y3-7 + PhD LINK

Quotes
> "Every surgeon must have a little internist in them and vice versa if they are going to be master in their field"
> "A wrong decision is generally less disastrous than indecision"
> "Half of graduate medical students become GPs"

Upshot
I've gone for orthopaedics for this specialist placement (I'll give it a go with the meatheads and hopefully practice some of the suturing we've been learning), with a backup choice in hand surgery (which is a part of orthopaedics anyway) as a close second.  With luck it'll be good exposure for ruling in / ruling out.

I'll have to book in those days in infectious disease when I have a gap.  And try for now to ignore the stats which suggest I'll eventually end up as a GP anyway...

Orthopaedics: neck, shoulder, hand, hip, knee, ankle
Infectious disease: pathogens
Cardiology: arterial stent (widens artery at blockage)

Saturday, 30 January 2016

Medical context - piano playing injuries

Ageing hands at the piano
I do like to tinkle out a few tunes on the piano, and latest excitement has been with duets.  For this you can buy specialist 2-person sheet music (exploring classical tunes is all the more fun with a beautiful woman to play with).  Alternatively - tough songs are easier with four hands (here's a jazzy one I'm trying).  The charm of a duet is you get good company, and you only have to do half the work!  So, to keep the interest going, I headed to a Joplin ragtime recital out in Nottingham featuring a little Atwell (great) and a Bowie tribute.  Now, chatting with the pianist post-gig, it turned out he was a little anxious about his hand problems, with a wonky thumb and some pain - understandably so.  And the question of medical advice came up.  But, much as we've covered hands in lectures, I had no specific medical context to help out!  So here's an attempt at targeted activity research...
Context of piano playing injuries:
The more you play (and the higher level you play at) the more likely you are to become injured. LINK (2010) - p.61.  Prevalence of ongoing injuries in professional musicians seems to be greater than 50%.

Piano players' common occupational ailments LINK (2010) - p.62
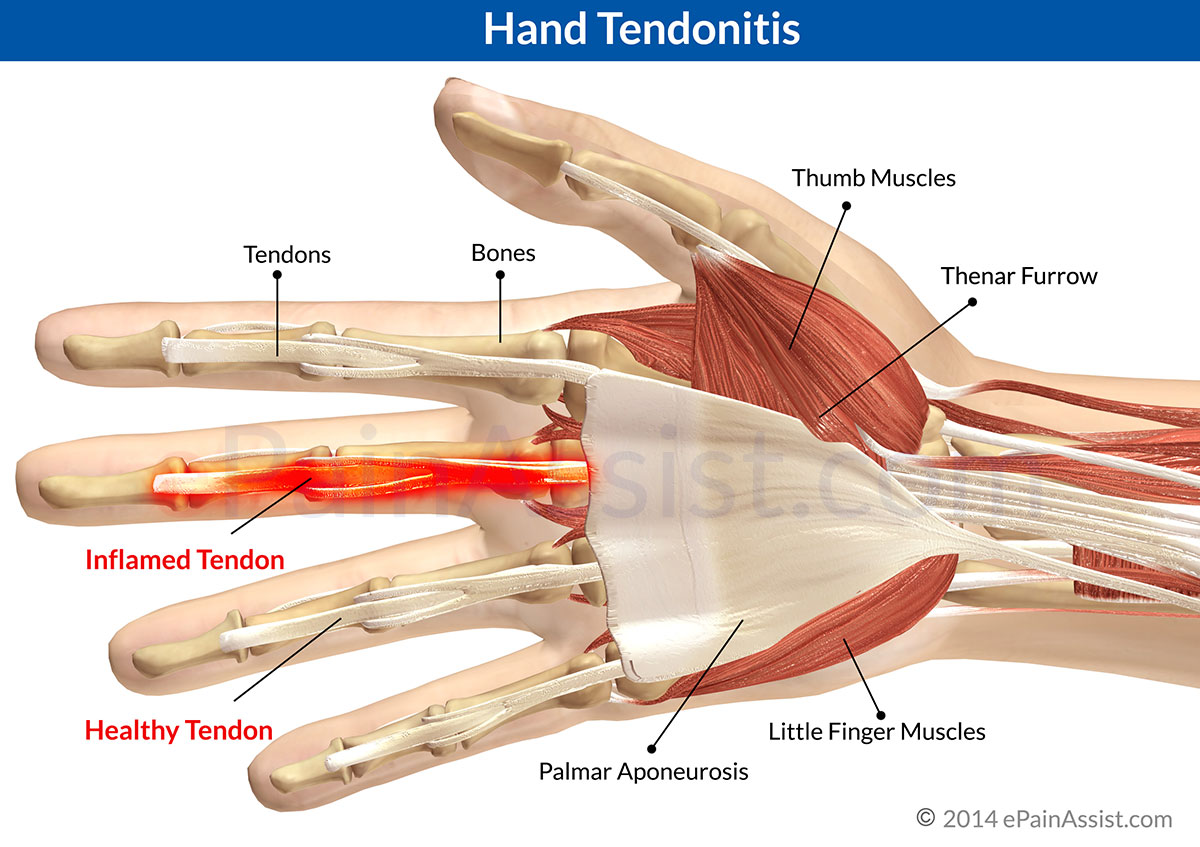
1) Tendinitis - inflammation of tendons
2) Overuse syndrome / RSI (not necessarily an accepted diagnosis) - degeneration of tendons/ligaments/nerves as rate of injury > rate of healing;  LINK
3) Carpal tunnel syndrome - median nerve trapping in the carpal tunnel of the wrist
4) Radial nerve compression syndrome - particularly entrapment of radial nerve at elbow
5) + Osteoarthritis - degenerative changes to hand/wrist joints due to overuse LINK (1984)

Abducted (splayed out) fourth and fifth fingers most likely to be damaged LINK (1989) - p.108
Extended wrist play causes damage, as do fortissimo and octave play LINK (1998) - p.11

Treatments
NB: these are remarkably similar to one another
1) Tendinitis: avoid rapid increase in tendon use; splinting and rest; painkillers; steroid injections.
2) Overuse syndrome: rest and anti-inflammatories; + potential use of ?quack massage therapy (ART) which describes a rather simplistic pathophysiology LINK
3) Carpal tunnel syndrome: splinting and rest; steroids; carpal tunnel release surgery LINK
4) Radial nerve compression: splinting and rest; steroids; surgical release of nerve along its course LINK
5) Osteoarthritis: rest, pain-based treatment and potentially joint replacement LINK

Additional advice
> Most piano-playing hand disorders are due to the mechanical process of learning and playing; non-expert doctors are ill-equipped to be able to offer helpful advice about how to resolve these problems; experienced piano teachers are more likely to be able to do so based on their own experience LINK
> Resting within and between practice sessions enables removal of metabolic waste products and replenishment of phosphocreatine, ATP, acid/base balance, resting membrane potentials ?weak LINK
> Resting during practising also enhances procedural memory retention LINK
> If you're overstretching with your small hands, you can either pick tunes with smaller spans, or there are people out there who'd like to sell you a smaller-size ergonomic piano, sounds sensible enough, if a little inconvenient to transport to performances! LINK


Tendinitis in the hand LINK
Carpal Tunnel Release
Joint changes in osteoarthritis of the hands LINK

'Play Me I'm Yours' street piano duet - Toronto

Sunday, 24 January 2016

Health behaviours influence life expectancy much more than quality of medical care

Dahlgreen Whitehead Model of Health (1991)
Our medical course is satisfyingly broad beyond the physical science - they even have us considering the sex lives of the elderly (all part of a healthy lifestyle, but lots of chlamydia & lack of partners tends to hold many of them back though, apparently).  All the talk of public health rang a bell in my head from psychology days about the importance of health-promotion and the limits of medical care to help.  So I wondered, well, since part of the reason we're in this is to have an impact, just what impact does medical care have on health, relatively speaking?

One meta-analysis [LINK] indicates that health-related behaviour accounts for 40% of early deaths in the US, genetics 20%, stressful social circumstances (e.g. income inequality, discrimination, lack of social relationships 20% (LINK1 LINK2 - together approx equivalent to tobacco smoking)), physical environment 10%, while early death is influenced only to a limited extent by the quality of medical care (10% of deaths).  The challenging message for us trainee doctors is 'public health is much more important than your hospital interventions'.  So - I briefly reviewed the research to see if these stats hold up.  They seem to!  


1) Research papers about common diseases, their causes, and historic changes in life expectancy 
(give qualitative support to the statistic)

The diseases which cause the greatest number of deaths - UK
Ischaemic heart disease (12%), Dementia & Alzheimers (~10%), Stroke (~6%), Lung cancer (~6%), Chronic lower respiratory infections (~5%) (together account for 41% of deaths)

The risk factors which cause the greatest number of early deaths - Europe
Tobacco smoking - 15% of all deaths; Other cardiovascular risk factors: hypertension, obesity, low physical activity/obesity, high blood glucose, high cholesterol, low fruit & veg intake - 25% of all deaths (together smoking and cardiovascular risk therefore account for 40% of deaths)

The diseases which cause the greatest number of years lived with disability (DALYs) - UK
Cancer (14%), Ischaemic heart disease (10%), Depression (8%), Stroke, (6%), Road Traffic accidents (4%), Direct effects of alcohol use (4%) - together account for 46% of years lived with disability

Contributing non-medical factors to disease/death pre-20th century (life expectancy has increased by 25 years across the 20th century):
- people weren't aware that tobacco smoking was bad for your health
- people weren't aware that a balanced diet was required for health
- people weren't aware that exercise was good for your health (idleness)
- widespread slum housing (squalor)
- deaths at work
    
Contributing medical factors pre-20th century:
- infant and maternal mortality perinatally (which can now be resolved by obstetric care and vaccination)
- hypertension (which can now be modified by exercise, smoking cessation and diet, as well as being assessed and controlled medically)
- infection (which can now be controlled by antibiotics)


2) Back-of-envelope calculations on Quality of Life and behaviour:
(give quantitative support to the statistic)

NHS - £110bn budget, NICE guidelines indicate acceptable spends vary between £0-30k per QALY (Quality-adjusted-life-year), therefore 11m QALYs saved per year if £10k per QALY is assumed.

AND

Sedentary lifestyle, i.e. lack of exercise: 7 QALYs lost per sedentary patient -> 60% prevalence -> 252m QALYs
Smoking: 10.5 QALYs lost per heavy smoker -> 20% prevalence -> 120m QALYs
Obesity: 5 QALYs lost per obese patient -> 25% prevalence -> 75m QALYs
High alcohol consumption: 4 QALYs lost per heavy drinker -> 15% prevalence -> 34m QALYs

Total on these factors - 470m QALYs (may be some double counting, but this is 40x the amount of QALYs seemingly accounted for by NHS interventions)

QALYs cost (from a Scandinavian study) http://www.ncbi.nlm.nih.gov/pubmed/17852988


3) Conclusion:
Based on these data, health behaviours in the UK have a far greater impact on life expectancy and quality of life than does the quality of medical care.  Challenging!  A good incentive to encourage our patients to get active, stop smoking, and lose weight.

Causes of death in the UK (2014) - ONS
Risk factors for death with high income Europe highlighted - WHO (2009):
Smoking - 15% of the 3.8m total deaths
The other cardiovascular factors are combined elsewhere in the research paper to give the 25% figure

Monday, 14 December 2015

Robotics in surgery

Robotic surgical theatre mock-up

I sat with my housemates Sam and Sabrina down in London over dinner one wintery night with Sabrina's lawyer father, and up came the conversation about robotics 'being the future', and the role of human surgeons being in gradual decline.  Challenging!  Could surgeons really be in one country while a robot operates in another, or could the blood-and-guts part of the profession become the realm of programmers?   Something of a career risk as a trainee doctor considering surgery.  How does the marketing hype about robotic surgeons hold up to the evidence?


Usage of robots in surgery: 
The market-leading surgical robot manufacturer (Intuitive Surgical - the Da Vinci robot) report 600,000+ operations per year globally using robots in 2015.  To put this in some context, there were 3.7 million surgical procedures in the UK in 2013/14

Intuitive surgical's marketing is supposedly excellent, and the limited US regulation of medical device advertising means that a market can be built for a product without there necessarily being a patient benefit. In a competitive hospital market, the prospect of robots to do your surgery is a differentiator for the patients. Bloomberg have a good article on this here


Conclusion:
Robot use is growing fast

Potential added value that robots can provide [LINK (2004)]
> Removing operator tremor
> Dexterity
> Technical solutions to microsurgery - operating on tiny blood vessels that might otherwise prove too challenging to reconnect (I find this particularly compelling)
> Ergonomic positioning of the surgeon
> 3D vision (better than on a typical laparoscopy screen)
> Decision support tools (i.e. an MRI overlay helping stereotactic needle placement)
> Automatic movement of instruments in synchrony with a beating heart

Conclusion:
The potential benefits to robot-assisted surgery are significant; but probably dependent on the extent to which the current practical limitations actually impact patient outcomes

Cost implication of robotic laparoscopy compared to conventional laparoscopy:
Per surgery additional cost:
+$200 per cholecystectomy (2014)
+$1,400-$2,200 per hysterectomy (2010)
+$2,500-$3,500 per nephrectomy/partial nephrectomy/pyeleoplasty (2011)
+$800 per radical prostatectomy (2011)

Individual outlay per robot
Net cost of DaVinci robot - $1.75 m, and when factored across their lifespan of use they have implications for the costs of each surgery performed.
Conclusion
Robot-assisted laparoscopy is currently more expensive than conventional laparoscopy.


History of surgical robot development: [LINK]
1983 - Arthrobot (holds limb during surgery)
1985 - PUMA560 (places needle for brain biopsy using CT)
2003 - Intuitive Surgical (DaVinci robot creator) merges with Computer Motion (Zeus/Aesop robot creators). Intuitive Surgical are now the leading robotic surgery technology company.

Conclusion:
Robots aren't a new thing in surgery - they've been around for 30+ years


Patient outcomes of robot use: 
In general for surgery, robots are ​more expensive, have more complications, and outcomes are not improved over laparascopic surgery based on 4000 studies [LINK].  NHS England consider there to be no mortality gains but some quality of life gains in prostate surgery with robots [LINK].  Cancer Research UK consider there to be no advantages yet in prostate surgery with robots [LINK]

Conclusion:
The evidence doesn't currently suggest that there are consistent patient benefits from robotic surgery


General conclusion
Robot use in surgery use is on the rise, and the potential for robots to enhance the quality of surgery certainly sounds impressive.  However, robots are expensive and currently of unproven benefit, so it's not yet time to be requesting your surgeon uses a robot rather than more traditional techniques.


Some videos of robots at work:
Example: Da Vinci Robot: peeling a grape
Animation: radical prostatectomy.
Prostate removal @2:00; bladder-urethra reattachment @ 3:00
Da Vinci Robot: radical prostatectomy

Light ?dark? relief:

Monday, 7 December 2015

Medical museums

Recommendations for places to immerse yourself in medicine:

Been to
1) The Wellcome Collection - London (beautiful reading room upstairs with names of the greats on the wall below the gallery.  Huge library and cross-cultural insights into medicine through history.  Obscure collections include African/European statuettes of erotica!
Wellcome Collection Reading room
2) Royal College of Surgeons Hunterian Museum - London (excellent history of surgery, as well as cabinets of surgical devices and obscure pathological cases.
Irish giant at the Hunterian
3) RCS Wellcome Museum of Anatomy & Pathology - London (amazing space, with healthy specimens lined up next to pathological ones.  NB: only open to those in the medical profession, including students; no photos
Study zone at Wellcome Anatomy & Pathology museum - free suturing practice available

4) Semmelweis Museum of Medical History - Budapest (has two collections - a medical history one in memory of Ignaz Semmelweis one of the fathers of antiseptic technique, whose unfortunate approach didn't win him much support while alive, has wonderful full-body medical wax models from the 16th century; second collection is of Hans Selye's extraordinary work into stress / coping / resilience and its effect on the body).

Susini's Anatomical Venus @ Semmelweis - c. 1790s.  Body hasn't changed much!

5) The Old Operating Theatre & Herb Garret - London (history of surgery in London - an example of how things were done in the past, and how lessons were learned from the mistakes)
Old Operating Theatre by Guy's Hospital - looks just like that featured in The Knick

6) Body Worlds - the one of Gunther von Haagens pedigree, currently on tour the USA, Germany, Poland, Netherlands (excellent for anatomical insight, a mixture of human and animal plastinated models)
Body Worlds - exhibition full of curious poses


Future plans!
Freud Museum - London
Maguro Parasitological Museum - Japan


Links:
London Medical Museums: http://medicalmuseums.org
Medical Museums of the world: http://www.mnn.com/lifestyle/arts-culture/photos/7-unusual-medical-museums/weird-science
Semmelweis Meseum: http://www.semmelweis.museum.hu/muzeum/index_en.html

[will keep this updated]

Hand surgery - an introduction

Since having shadowed a hand surgeon in Derby, which got me excited about the profession, I thought I'd review how hand surgery is organised, and just what hand surgeons do.

Hand surgery governing body - the BSSH
The British Society for Surgery of the Hand (BSSH), est 1952, formally 1968.  Its first president was Irish-born 'Guy Pulvertaft' (1907-1986).  The Pulvertaft Hand Centre at the Royal Derby Hospital of the Royal College of Surgeons (internationally recognised) is named after him.

Commonest hand surgeries
I was informed during shadowing at the Pulvertaft that there are 250 hand surgeries that can be mastered.  BSSH list the commonest as (2006 UK figures):
- Carpal tunnel decompression (38,000)
- Palmar fasciotomy for Dupuytrens disease (11,000)
- Surgical removal of Ganglion cysts (6,400)
Carpal Tunnel Release

Ganglion cyst
Dupuytrens

Further surgeries
These include the following - it would be good to find a resource with a list including statistics
- Trigger finger release
- Post-traumatic reconstructive surgery of the hand, including scaphoid (wrist bone) fracture
- Ruptured tendon repair, often secondary to rheumatoid arthritis - plus tendon transfer
- Trapeziectomy (removal of a bone in the wrist) at the base of the thumb
- Joint fusions (PIP, DIP, carpal fusion in the wrist)
- Arthroplasty (e.g. resurfacing joints - commonly MCP, PIP)
- Treatment for ligament injuries in the wrist
- Wrist replacement, nerve ablation, very specialised centres conduct hand transplants, etc. unclear how common all these are

Referrals to hand units
Referrals to hand units don't all require surgical intervention - common referrals are below:
Links:
BSSH Hand surgery report: http://www.bssh.ac.uk/members/documents/ukhandsurgreport.pdf
Introduction to common hand surgeries for junior doctors: http://bit.ly/1m7pTNJ

Upper extremity prostheses

I was interested to see what was available in prosthetic devices for upper limb injury, after having visited a prosthesis manufacture workshop in Nairobi in summer 2015, and also since I have an interest in hands.

Prosthesis options:
Passive prosthetics - cosmetically helpful but without significant functional use (some can be reshaped into a pincer grip) http://biomed.brown.edu/Courses/BI108/BI108_2003_Groups/Hand_Transplantation/altern2.html

Functional prosthetics 1 - simple mechanical cable operated - can operate by motion to close the gripping device, which would reopen by an elastic mechanism (e.g. rubber banding).  Limited in those patients with limited movement.  Paired claws and pincers are remarkably functional and offer good visual feedback of what the hand is doing, thus enhancing their use.  Cheaper to produce.


Functional prosthetics 2 - myoelectric - skin-based electrodes sense muscle contraction, and thus enable the device to be controlled.  Devices tend to be heavy, expensive and battery duration can be an issue.   https://www.youtube.com/watch?v=_qUPnnROxvY


Particularly impressive is the variety of grips with the advanced versions of these prostheses:
o    Handshake
o    Power grip
o    Precision grip
o    Mouse grip (e.g. to point and click)
o    Trigger operated device grip
o    Index finger use for PIN number entry

o    Key-holding grip

‘The Hunger Games’ Actress fitted with new bebionic hand


Notable figures with upper extremity prostheses:
Rick Allen – Def Leppard drummer (RTA amputee)
Aron Ralston – Adventure writer featured in 127 hours film (amputated his own right arm after becoming trapped by a boulder)
Abu Hamza – radical Islamic cleric known for using a pair of hooks (explosives accident)
Matthew Scott - first recipient of a lasting hand transplant, which is still functional more than a decade later (firework explosion).

Blog link 
Great thoughts on prosthetics and exoskeletons
https://forrestbrown.co.uk/news/we-are-all-cyborgs/ 

About Me

My photo
Medical student, keen on travel, piano, and the outdoors. Past work in psychological research and healthcare IT consulting.